


Description
Memantine HCl Nootropic Liquid








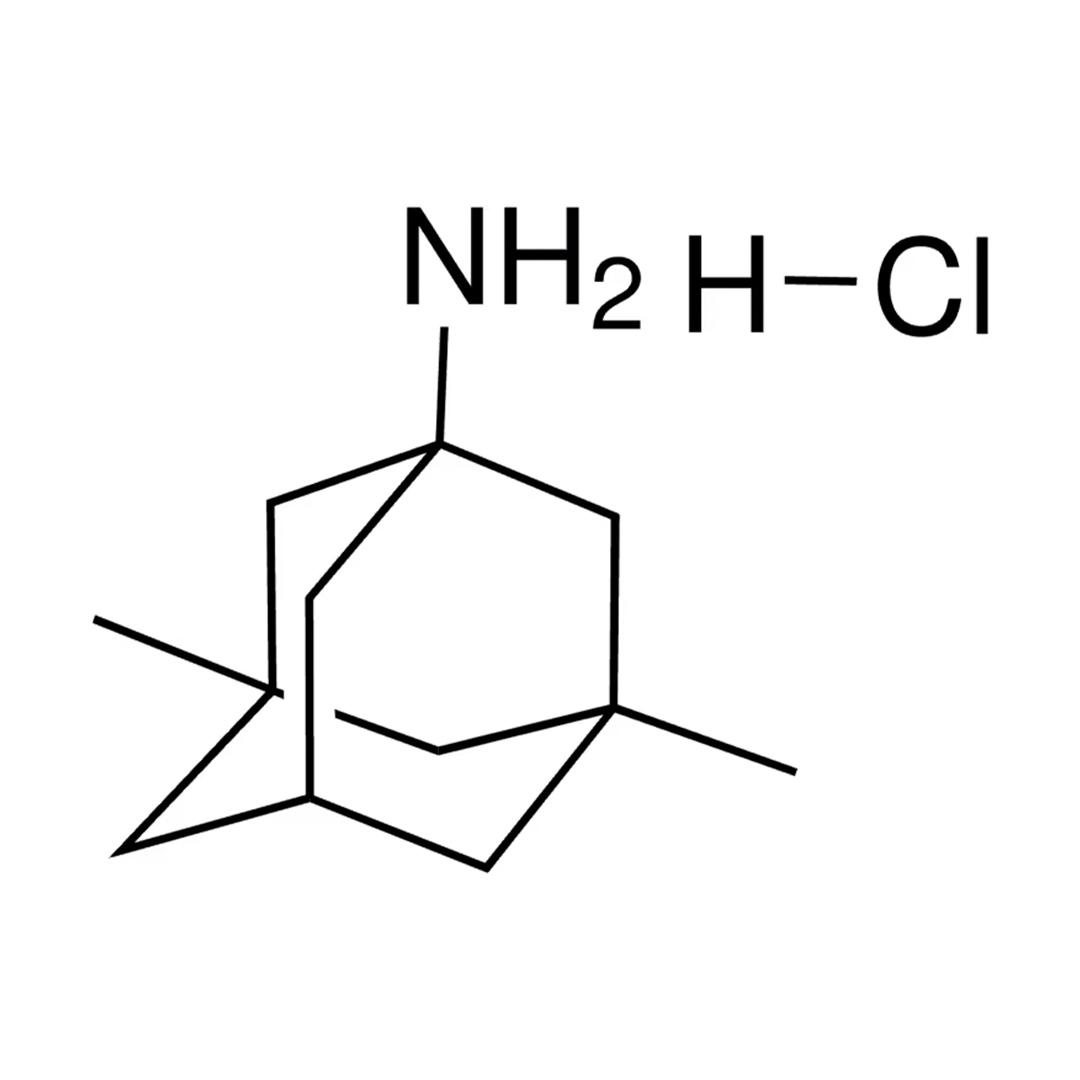
| CAS Number | 41100-52-1 |
| Other Names | 3,5-Dimethyl-1-adamantanamine hydrochloride, 3,5-Dimethylamantadine hydrochloride, 3,5-Dimethyltricyclo[3.3.1.13,7]decan-1-amine hydrochloride, Memantine hydrochloride |
| IUPAC Name |
Hydrogen 3,5-dimethyladamantan-1-amine chloride
|
| Molecular Formula | C₁₂H₂₁N•HCl |
| Molecular Weight | 215.76 |
| Purity | ≥99% Pure (LC-MS) |
| Liquid Availability |  30mL bottle (10mg/mL, 300mg total) |
| Powder Availability | 10 grams
|
| Gel Availability | N/A |
| Storage | Store in cool dry environment, away from direct sunlight. |
| Terms | All products are for laboratory developmental research USE ONLY. Products are not for human consumption. |
What is Memantine?
Memantine is a nootropic agent with neuroprotective qualities that has been primarily used in the treatment of moderate to severe Alzheimer’s disease. As an uncompetitive antagonist of the N-methyl-D-aspartate (NMDA) receptor, memantine works by regulating glutamatergic activity in the brain, which is often disrupted in neurodegenerative disorders. By blocking excessive activation of NMDA receptors, memantine helps to reduce excitotoxicity. This mechanism of action makes memantine distinct from other Alzheimer’s medications, such as acetylcholinesterase inhibitors, and has also prompted interest in its other potential uses, including applications in Parkinson’s disease, multiple sclerosis, depression, and other cognitive disorders. Memantine’s ability to preserve and potentially enhance cognitive function has made it a subject of increasing interest in neuroscience and psychopharmacology.
Main Research Findings
1) Treatment with memantine was found to reduce clinical deterioration in moderate-to-severe cases of Alzheimer’s disease.
2) Patients receiving whole brain radiotherapy experienced a delayed time to cognitive decline, and reduced degeneration rate of memory, executive functioning, and processing speed following treatment with memantine.
Selected Data
1) This clinical trial conducted by the research team of Reisburg et al investigated the efficacy and safety of memantine, a nootropic compound, in treating community-dwelling patients with moderate-to-severe Alzheimer’s disease. Participants were aged 50 or older and met the criteria for probable Alzheimer’s disease as defined by both the DSM-IV and the National Institute of Neurologic and Communicative Disorders and Stroke–Alzheimer’s Disease and Related Disorders Association (NINCDS–ADRDA). To qualify, patients needed Mini–Mental State Examination scores between 3 and 14, indicating significant cognitive impairment, and were required to be in stages 5 or 6 on the Global Deterioration Scale. Additionally, participants had to be at stage 6a or higher on the Functional Assessment Staging Instrument, which signifies impairments in basic activities of daily living. Patients were also required to have a reliable caregiver and have undergone brain imaging within the past year [1] .
Exclusion criteria included the presence of vascular dementia or any other neurological disease aside from Alzheimer’s, major depressive disorder, or a modified Hachinski Ischemic Rating Scale score greater than 4, which would indicate potential cerebrovascular disease. Patients were also excluded if they had any significant comorbid medical conditions or abnormal lab values. Furthermore, individuals taking certain medications including anticonvulsants, antiparkinsonian drugs, neuroleptics, cholinomimetic agents, or other investigational compounds were not eligible. However, patients on a stable dose of antidepressants for at least two months prior to the trial were allowed to participate. Use of chloral hydrate was permitted as a sedative, but not within 24 hours of any study assessment [1].
The study was designed as a 28-week, randomized, double-blind, placebo-controlled, parallel-group trial. Participants were randomly assigned to receive either 20 mg per day of memantine or an identical-appearing placebo. Randomization was stratified by site using a computerized system to maintain blinding. Treatment was discontinued if deemed medically necessary or if the patient chose to withdraw. If a patient withdrew early, they were encouraged to complete final evaluations and return for a “retrieved-dropout” visit at week 28. This visit included all the primary endpoint assessments to preserve data integrity. An optional 24-week open-label extension, in which all participants received memantine, was offered following the main study, although results from that phase were still under analysis.
Two co-primary efficacy endpoints were established. The first was the Clinician’s Interview-Based Impression of Change Plus Caregiver Input (CIBIC-Plus), a global assessment that captures overall patient status relative to baseline on a 7-point scale. It includes information from structured interviews with both the patient and the caregiver and evaluates cognition, function, and behavior. Clinicians conducting these interviews were blinded to treatment assignment and consistent across all time points for each patient whenever possible. The second primary endpoint was the Alzheimer’s Disease Cooperative Study–Activities of Daily Living Inventory, modified for severe dementia (ADCS-ADLsev). This 19-item caregiver-rated tool measures a patient’s ability to perform basic daily tasks, with total scores ranging from 0 to 54, where higher scores indicate better functioning [1].
In addition to the primary endpoints, several secondary outcomes were assessed to provide a more comprehensive understanding of treatment effects. These included the Severe Impairment Battery (SIB), which evaluates cognitive domains in patients with severe dementia; the MMSE, which provides a general measure of cognitive function; the Global Deterioration Scale, which evaluates overall cognitive and functional decline; and the Functional Assessment Staging Instrument, which tracks the progressive loss of daily functional abilities. Neuropsychiatric symptoms were measured using the Neuropsychiatric Inventory, which also captures caregiver distress, and caregiver burden and resource use were assessed through the Resource Utilization in Dementia instrument. A predefined responder analysis classified patients as responders if they showed no decline or improvement on the CIBIC-Plus along with stability or improvement on either the ADCS-ADLsev or the SIB [1].
Safety monitoring was an integral part of the study. Patients underwent regular neurologic and physical examinations, as well as vital sign checks, electrocardiograms, and laboratory tests including blood chemistry, hematology, and urinalysis. Adverse events were carefully recorded throughout the study period.
Statistical analyses followed an intent-to-treat approach and included all randomized patients who had at least one post-baseline assessment. For participants who discontinued early, their last available data point was carried forward to the week 28 endpoint. Three additional sensitivity analyses were conducted to address missing data: one used retrieved-dropout values at week 28, another assumed no change for patients with no post-baseline data, and a third replaced missing values with the mean decline observed in the placebo group. An observed-cases analysis, which included only patients who completed the 28-week visit, was also performed. Efficacy results were analyzed using the Wilcoxon–Mann–Whitney test, a non-parametric method suitable for independent samples. All statistical tests were two-sided, and no interim analyses were conducted [1].
In summary, this clinical trial aimed to assess the efficacy and safety of memantine in individuals with moderate-to-severe Alzheimer’s disease living in the community. By employing stringent inclusion criteria, comprehensive outcome measures, and rigorous statistical methods, the study provided valuable insight into memantine’s potential as a therapeutic option for patients at this advanced stage of dementia [1].
2) This clinical trial performed by researchers Brown et al, evaluated the potential neuroprotective effect of memantine in patients with brain metastases receiving whole-brain radiotherapy. Eligible participants were adults with a confirmed diagnosis of a solid malignancy within five years of enrollment and radiographically evident brain metastases on contrast-enhanced MRI, or CT if MRI was not feasible. Additional inclusion criteria required patients to have a Karnofsky Performance Status score of at least 70, indicating they were able to care for themselves, and stable systemic disease for the preceding three months. Laboratory values were used to screen for renal and hepatic function, with eligibility restricted to patients with serum creatinine ≤3 mg/dL, creatinine clearance ≥30 mL/min, total bilirubin ≤2.5 mg/dL, and blood urea nitrogen <20 mg/dL. A Mini-Mental State Examination score above 18 was also necessary, to ensure patients had sufficient cognitive function for assessment [2].
Patients were excluded if they had allergies to memantine, active substance abuse, chronic benzodiazepine use, or any severe comorbid conditions. Previous treatment for brain metastases with surgery or radiosurgery was allowed, but prior cranial external beam radiotherapy was not. Patients undergoing systemic therapy could participate if they had completed such treatment at least 14 days prior to the study, and they were required to delay any new chemotherapy until at least 14 days after the completion of radiotherapy. All patients gave informed consent, and the study protocol received approval from the institutional review boards of all participating centers [2].
The study design employed a randomized, placebo-controlled format using the Zelen allocation method. Patients were stratified by Recursive Partitioning Analysis class I or II, and whether they had undergone surgery/radiosurgery within eight weeks or had no prior surgical treatment. Within each stratum, patients were randomly assigned in a 1:1 ratio to receive either memantine or placebo.
The treatment protocol consisted of whole brain radiotherapy administered in 15 fractions of 2.5 Gy for a total dose of 37.5 Gy. Patients began taking the study drug no later than the third day of whole brain radiotherapy. Memantine or placebo was administered over 24 weeks, with a dose escalation schedule during the first four weeks. The initial dosage was 5 mg once daily in week 1, increasing to 5 mg twice daily in week 2, 10 mg in the morning and 5 mg in the evening in week 3, and reaching the target dose of 10 mg twice daily from week 4 onwards. Dosage adjustments were made based on renal function: it was reduced if creatinine clearance fell below 30 mL/min and withheld entirely if clearance dropped below 5 mL/min [2].
Participants underwent evaluations at baseline and at weeks 8, 16, 24, and 52 after starting the study drug. These assessments included neurological and physical exams, performance status measurements, brain imaging, laboratory testing including creatinine, BUN, and bilirubin, and neuropsychological testing. The neuropsychological battery assessed memory through the Hopkins Verbal Learning Test-Revised (HVLT-R), processing speed assessed by the Trail Making Test Part A, executive function evaluated by the Trail Making Test Part B, verbal fluency assessed by Controlled Oral Word Association, and general cognition evaluated by the MMSE. Previous research has demonstrated that changes in these metrics are associated with quality of life, independence, and clinical outcomes such as survival and disease progression [2].
The primary endpoint of the trial was the preservation of memory function, specifically delayed recall, as measured by the HVLT-R Delayed Recall at 24 weeks. Secondary endpoints included time to cognitive failure defined as the first instance of decline on any neurocognitive test, overall survival, progression-free survival, and adverse event assessment. Adverse events were reported using the Common Terminology Criteria for Adverse Events version 3.0.
The trial’s statistical foundation was based on previous studies showing a decline of 0.87 points in HVLT-R DR scores over 24 weeks following whole brain radiotherapy. It was hypothesized that memantine would mitigate this decline. Using a one-sided Wilcoxon rank-sum test with a significance level of 0.025, the study aimed for 80% power to detect this difference, requiring 221 patients per arm. To account for potential attrition, the target sample size was increased to 536 participants [2].
An intent-to-treat analysis was employed, including all randomized patients who met eligibility criteria. For patients unable to complete cognitive assessments due to neurological deterioration, the lowest possible scores were assigned. Additionally, missing values for surviving patients were imputed using the Markov chain Monte Carlo method. Cognitive performance was analyzed using both raw scores and standardized z scores. A composite score was derived from the average z scores of all cognitive tests, and decline was defined as either a 2-standard-deviation drop from baseline or a score change exceeding the Reliable Change Index [2].
Time to cognitive failure was analyzed using the cumulative incidence method, accounting for competing risks like disease progression and death. Gray’s test was applied to evaluate group differences at the 0.025 significance level. Cox proportional hazards models were used to estimate hazard ratios and 95% confidence intervals for treatment effects. For disease progression, criteria included a ≥50% increase in lesions ≤1 cm, ≥25% increase in lesions >1 cm, or new brain metastases. Death was also classified as progression. Progression-free and overall survival times were calculated using Kaplan–Meier methods, with group comparisons tested via a stratified log-rank test.
In summary, this randomized trial evaluated whether memantine could preserve cognitive function in patients undergoing whole brain radiotherapy for brain metastases. By including neurocognitive assessments, careful stratification, and detailed statistical analyses, the study aimed to determine if memantine could mitigate cognitive decline associated with cranial irradiation. The results of this trial contribute to understanding how best to protect brain function in patients with metastatic cancer undergoing radiation therapy [2].
Discussion
1) The clinical trial performed by the research team of Reisberg et al evaluated the efficacy and safety of memantine, a medication used to treat moderate-to-severe Alzheimer’s disease. The study enrolled 252 patients out of 345 screened individuals that were then randomly assigned in equal numbers to receive either memantine or a placebo. The trial was double-blind in design, meaning neither the patients nor the clinicians knew who received the active drug. Of the 252 enrolled participants, 126 were assigned to the memantine group and 126 to the placebo group. The baseline characteristics were well balanced across the two groups. Approximately two-thirds of the participants were female, and the average age was 76 years. The mean baseline score on the Mini–Mental State Examination, a commonly used test to assess cognitive function, was 7.9, indicating that the study population had moderate-to-severe cognitive impairment [1].
The efficacy of memantine was assessed using various tools, including the CIBIC-Plus, the ADCS-ADLsev, the SIB, the Functional Assessment Staging (FAST) scale, and the Resource Utilization in Dementia (RUD) score. Results showed a favorable trend for memantine in several efficacy measures. On the CIBIC-Plus scale, memantine demonstrated a modest benefit compared to placebo at week 28, with a mean difference of 0.3 points, indicating a statistically significant improvement from baseline. Similarly, patients in the memantine group experienced significantly less deterioration in daily functioning, as assessed by the ADCS-ADLsev. At both the study’s endpoint and week 28, the memantine group showed better outcomes with a mean difference of 2.1 points using the last observation carried forward analysis and a 3.4-point difference in the observed-cases analysis [1].
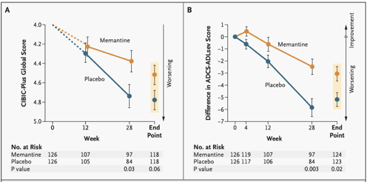
Figure 1: A) Changes in CBIC-Plus Global scores and B) differences in ADCS-ADLsec scores throughout the 28 week experimental period in the placebo-treated group and memantine-treated group
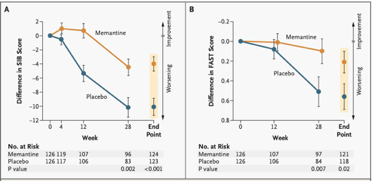
Figure 2: A) Differences SIB and B) FAST scores throughout the 28 week experimental period in the placebo-treated group and the memantine-treated group
In addition, performance on the SIB, which evaluates cognitive function in severely impaired individuals, significantly favored memantine. According to the study’s predetermined criteria for treatment response, 29% of patients in the memantine group were classified as responders, compared to only 10% in the placebo group.Memantine also slowed the progression of Alzheimer’s disease, as indicated by better scores on the FAST scale. However, there were no significant differences between groups in MMSE scores, Global Deterioration Scale stage, or the Neuropsychiatric Inventory, which evaluates behavioral symptoms [1].
Subgroup analysis revealed that memantine was beneficial across both moderate and severe Alzheimer’s disease categories, with improvements noted in all primary outcome measures regardless of initial cognitive severity. Furthermore, memantine significantly reduced the time burden placed on caregivers. Based on the RUD score, caregivers of memantine-treated patients spent approximately 45.8 fewer hours per month providing care.
In terms of safety and tolerability, adverse events were common in both groups with 84% incidence in the memantine group and 87% incidence in the placebo group; this is expected in a population with advanced disease. Most events were mild to moderate and not directly related to the study medication. The most frequently reported adverse events had similar incidence rates in both groups, differing by no more than 2%. No meaningful differences were observed between the two groups in terms of laboratory results, ECG findings, or vital signs, indicating that memantine does not cause significant physiological disturbances in this patient population [1].
In conclusion, the study demonstrated that memantine provides statistically and clinically meaningful benefit in patients with moderate-to-severe Alzheimer’s disease. It slows the progression of cognitive and functional decline, reduces caregiver burden, and has a favorable safety profile compared to placebo. These findings support the use of memantine as a therapeutic option for managing symptoms in this challenging stage of Alzheimer’s disease [1].
2) The randomized, double-blind clinical trial was conducted by the research team of Brown et al evaluated the effects of memantine in patients receiving whole-brain radiotherapy for brain metastases. The trial aimed to assess whether memantine could preserve cognitive function and improve clinical outcomes when administered alongside whole brain radiotherapy. After screening, 508 patients were deemed eligible for analysis, while 46 were excluded primarily due to elevated creatinine or BUN levels. The two treatment groups defined as those receiving whole brain radiotherapy plus memantine and those receiving whole brain radiotherapy plus placebo, were generally balanced in terms of baseline demographics, neurological function, and tumor characteristics, except for a slightly higher proportion of patients in the memantine group who were taking steroids at baseline [2].
The median age of participants was 59 years, with 56% being female. The most common primary cancer type at 70% was lung cancer. Steroid and chemotherapy use remained relatively stable throughout the study. Chemotherapy usage hovered around 29–33% at various time points, while steroid use declined over time, from 42% at 3 months to 24% at 12 months. Whole brain radiotherapy adherence was high, with 93% of patients completing treatment per protocol. Similarly, memantine and placebo compliance were comparable; 31% of patients in the memantine group and 33% in the placebo group completed all six months of drug therapy without modifications or delays [2].
Analysis of baseline characteristics revealed that patients who completed cognitive evaluations tended to have better prognoses, longer survival, and better neurological function. These patients were more likely to be classified as RPA Class I and to have undergone prior surgical resection or radiosurgery. Importantly, survival data supported this trend, with patients who completed cognitive assessments demonstrating significantly longer median survival times compared to those who did not. For instance, at the 8-week evaluation, median survival was 12.4 months for those completing assessments compared to just 2.7 months for those who did not.
Regarding cognitive outcomes, the primary endpoint focused on changes in delayed recall measured by HVLT-R DR scores at 24 weeks. The memantine group experienced a median decline of 0 in HVLT-R DR, whereas the placebo group had a median decline of –0.90, suggesting the benefits of memantine. Similar trends favoring memantine were observed at 8 weeks, however, statistically significant differences were found in several secondary cognitive outcomes. These included improved performance in HVLT-R Delayed Recognition, MMSE scores, and Controlled Oral Word Association (COWA) scores, with less deterioration observed in the memantine group [2].
Furthermore, the time to cognitive failure was defined as the first failure on any neurocognitive test, and significantly favored the memantine group. At 24 weeks, the probability of cognitive failure was 53.8% in the memantine group compared to 64.9% in the placebo group, reflecting a 21% relative reduction in risk.
Linear regression models were employed to adjust for baseline assessment scores and intracranial progression. These models reinforced the consistency of the findings. While no significant differences were observed in HVLT-R DR scores in complete-case analysis, a significant benefit in COWA scores at 8 weeks was observed in the memantine group. The influence of steroid use on cognitive outcomes was also assessed. The only significant difference emerged in the HVLT-R DR scores at 8 weeks, where patients on steroids had greater declines compared to those not on steroids of –2 vs. –0.5, respectively. This suggests that steroid usage might negatively impact cognitive function [2].
In terms of survival outcomes, there were no significant differences between treatment arms. The median progression-free survival was 4.7 months in the memantine group and 5.5 months in the placebo group (HR = 1.06; P = 0.27). Similarly, overall survival was 6.7 months for memantine and 7.8 months for placebo (HR = 1.06; P = 0.28). Thus, memantine did not adversely affect survival outcomes [2].
In summary, while memantine did not significantly improve the primary cognitive outcome measure, HVLT-R DR, due to limited statistical power, it showed consistent trends favoring cognitive protection across several secondary measures. It also significantly delayed time to cognitive failure and was well tolerated, without compromising overall or progression-free survival. These findings support the use of memantine to mitigate cognitive decline in patients undergoing WBRT for brain metastases, particularly given its favorable safety profile and the observed preservation of cognitive function over time [2].
Disclaimer
**LAB USE ONLY**
*This information is for educational purposes only and does not constitute medical advice. THE PRODUCTS DESCRIBED HEREIN ARE FOR RESEARCH USE ONLY. All clinical research must be conducted with oversight from the appropriate Institutional Review Board (IRB). All preclinical research must be conducted with oversight from the appropriate Institutional Animal Care and Use Committee (IACUC) following the guidelines of the Animal Welfare Act (AWA).
Citations
[1] Reisberg B, Doody R, Stöffler A, et al. Memantine in moderate-to-severe Alzheimer’s disease. N Engl J Med. 2003;348(14):1333-1341. doi:10.1056/NEJMoa013128
[2] Brown PD, Pugh S, Laack NN, et al. Memantine for the prevention of cognitive dysfunction in patients receiving whole-brain radiotherapy: a randomized, double-blind, placebo-controlled trial. Neuro Oncol. 2013;15(10):1429-1437. doi:10.1093/neuonc/not114
Memantine HCl is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions prior to ordering.






 Memantine in Neurodegeneration: Pharmacokinetics and Mechanism of Action


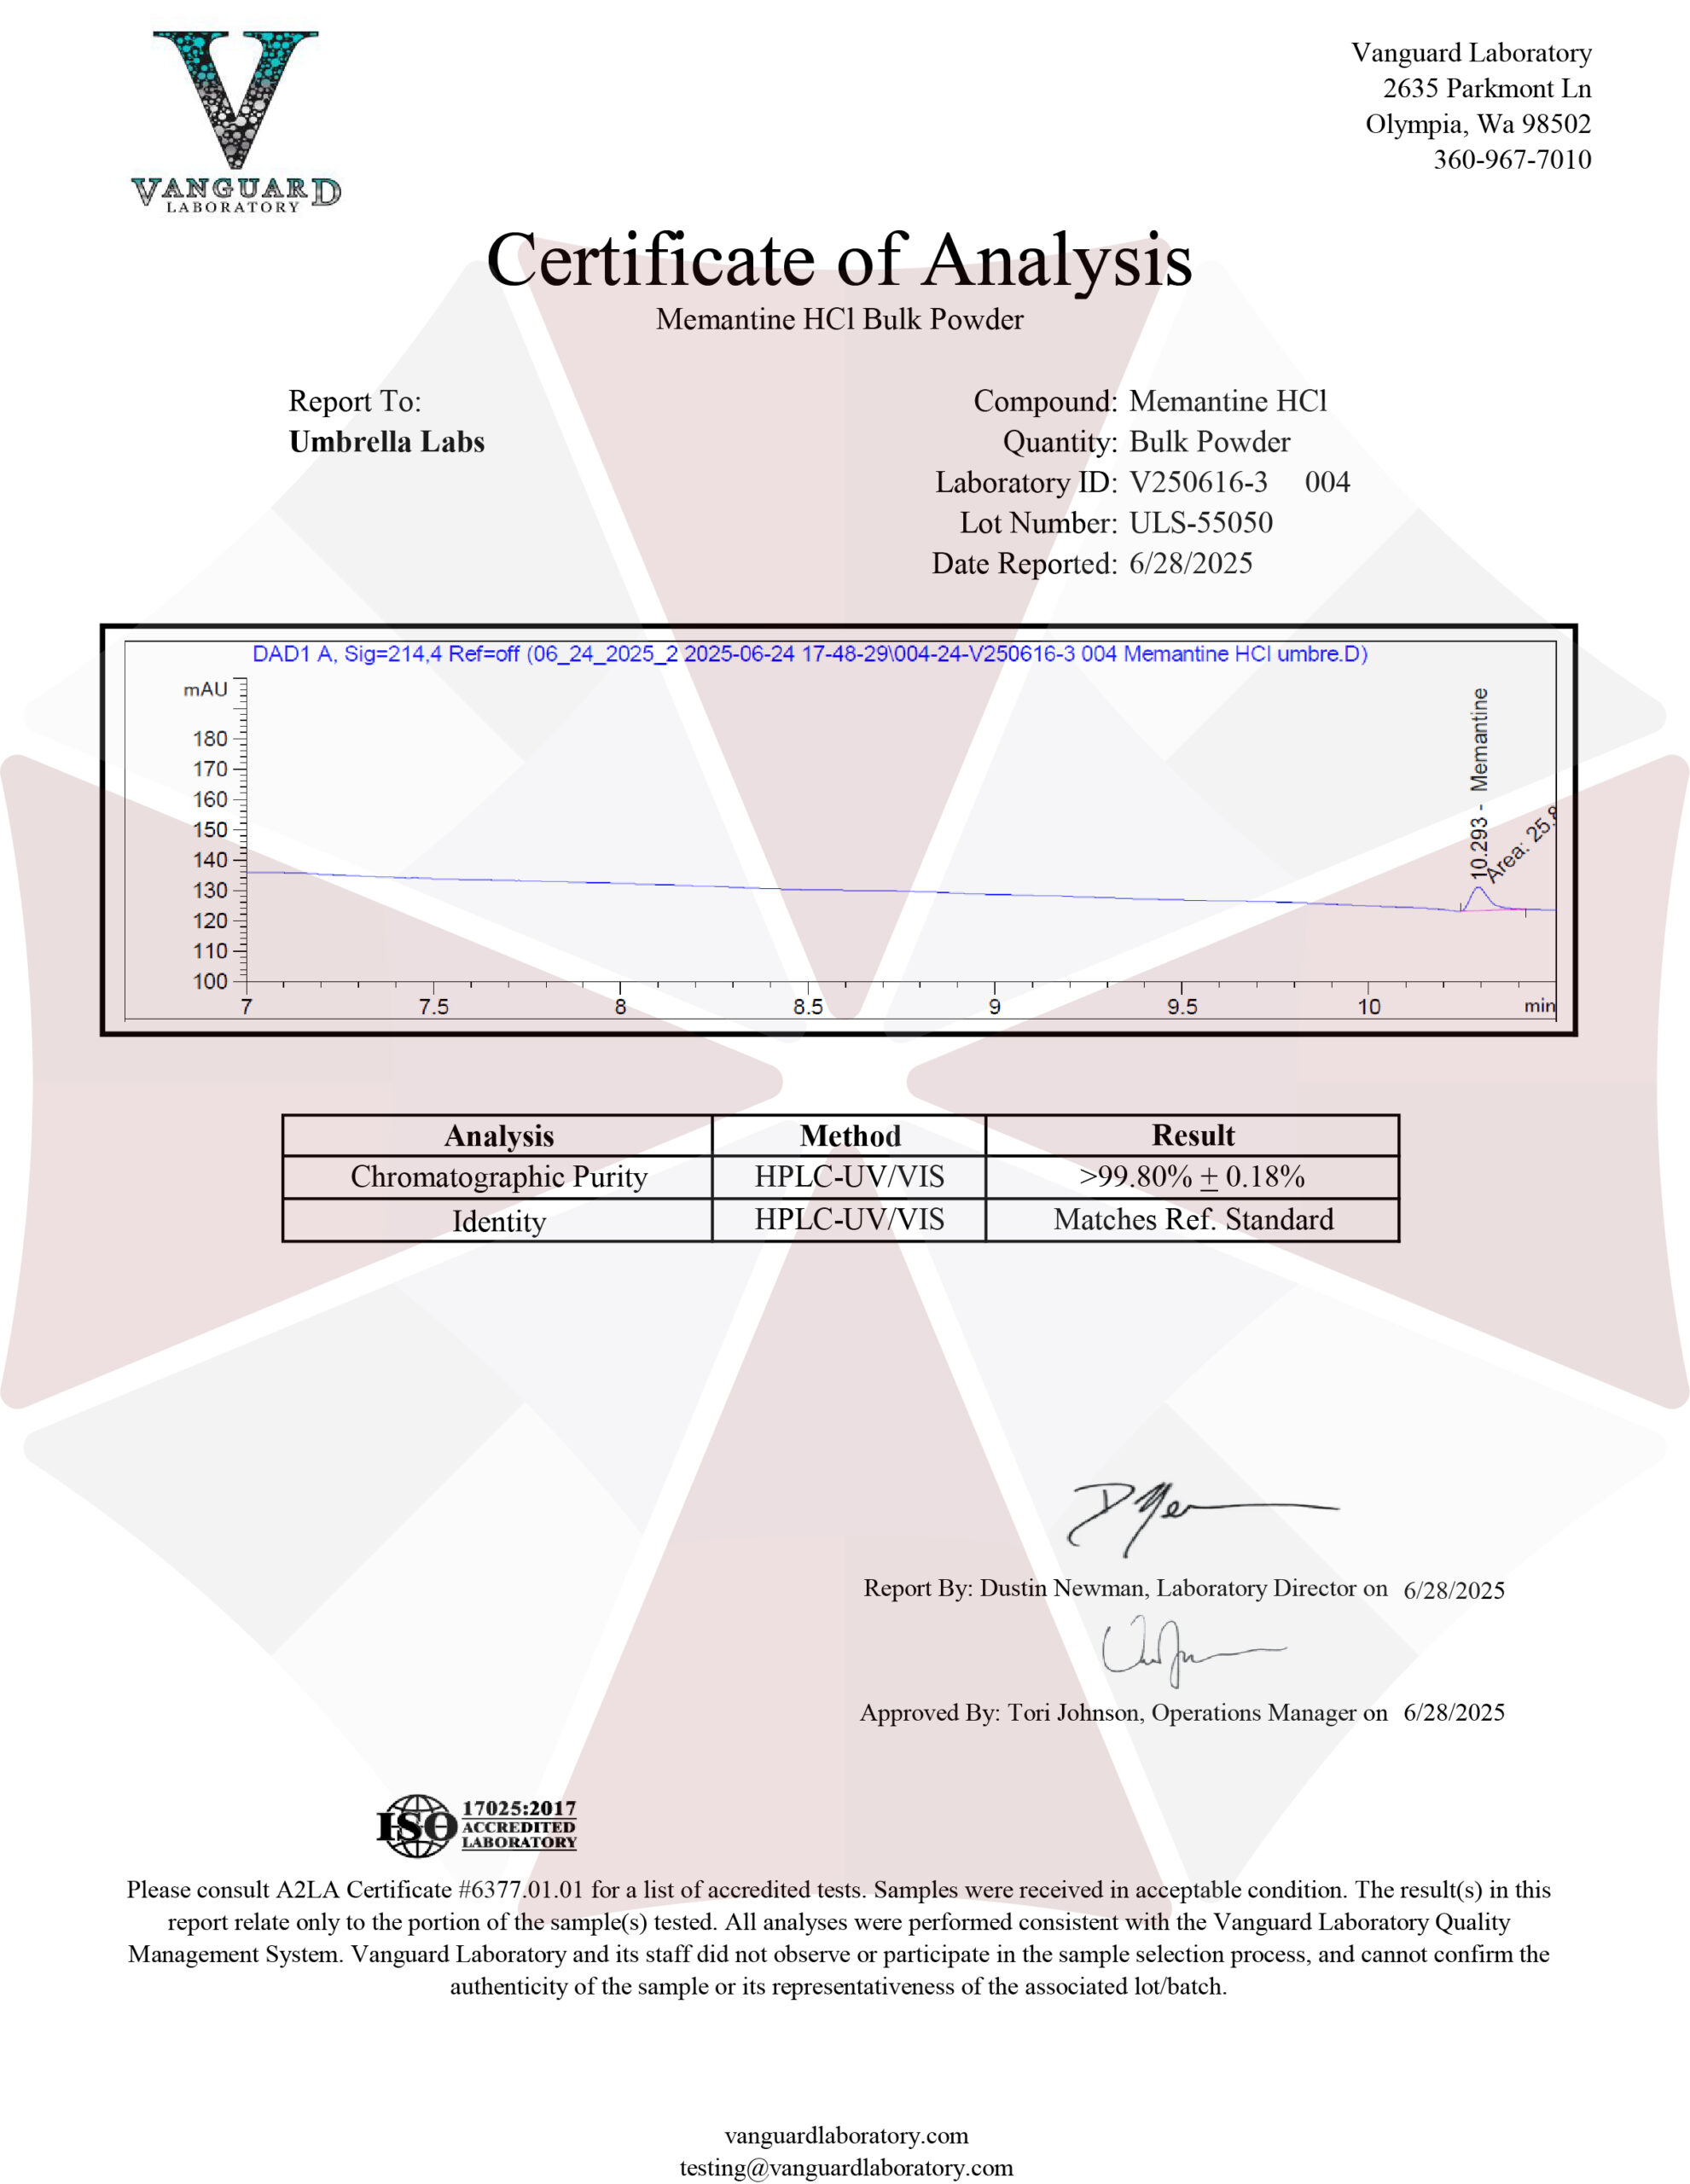
| File Name | View/Download |
| 2025-06-28-Umbrella-Labs-Memantine-HCl-Certificate-of-Analysis-COA.pdf | |
VIEW CERTIFICATES OF ANALYSIS (COA)



Reviews
There are no reviews yet.